


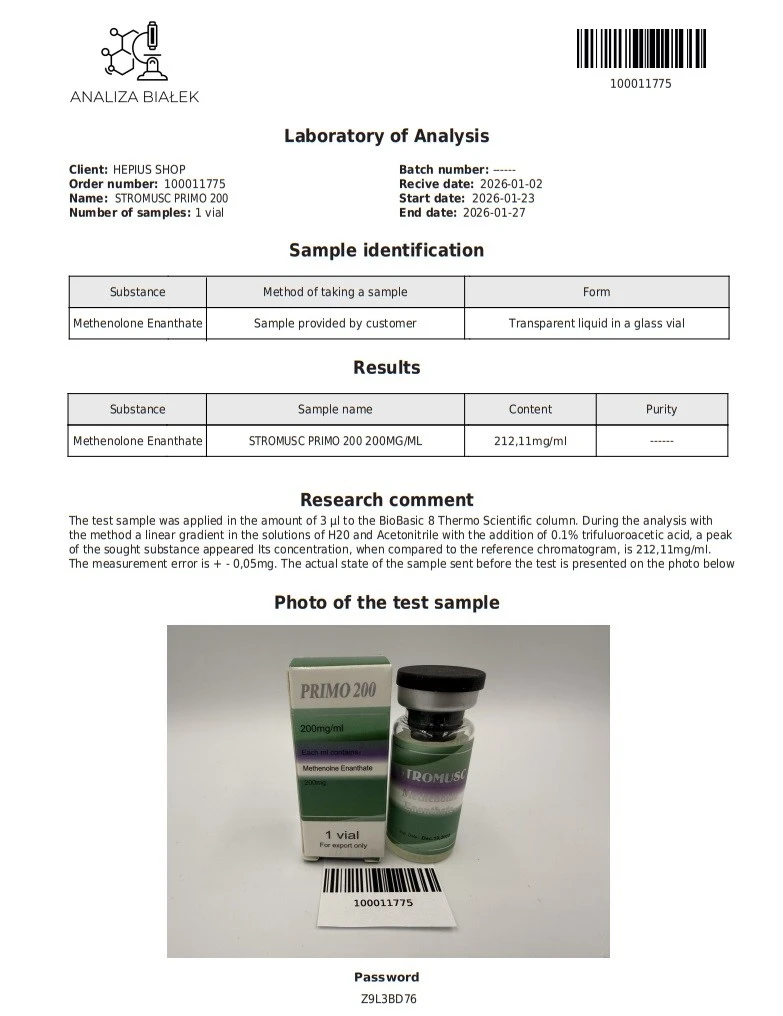
Premium Brand STROMUSC Primobolan(Methenolone Enanthate)200mg/ml For Bodybuilding CAS:303-42-4
Methenolone enanthate occupies a peculiar position in the anabolic landscape. It is neither the strongest nor the fastest-acting compound available, yet it has maintained a devoted following among physique athletes for more than half a century. The injectable version, commonly recognized under the trade name Primobolan Depot, has acquired a reputation as the “gentleman’s steroid”—a compound associated with clean, dry, sustainable gains rather than explosive mass or dramatic water retention. The 200 mg/ml concentration represents a more practical formulation for modern users, reducing injection volume while preserving the compound’s characteristic slow-release pharmacokinetics. This profile examines methenolone enanthate from a bodybuilding perspective, covering its chemical identity, pharmacological features, practical applications, dosage considerations, cycle design, half-life, and post-cycle therapy requirements.
What Methenolone Enanthate Is
Methenolone enanthate is a synthetic anabolic-androgenic steroid derived from dihydrotestosterone (DHT). Chemically, it is the 17β-enanthate ester of methenolone, formed by esterifying the parent hormone with enanthic acid (heptanoic acid). The addition of this ester is not a minor detail-it fundamentally alters the compound's behaviour in the body. While unesterified methenolone would be cleared relatively quickly, the enanthate ester renders it highly lipophilic, causing it to be absorbed slowly from the intramuscular injection site into the bloodstream. Once circulating, plasma esterases gradually cleave the ester bond, liberating the active hormone methenolone.
Methenolone itself is a 1-methyl derivative of DHT. This structural modification is significant: the methyl group at the C1 position confers resistance to hepatic metabolism while preserving anabolic activity. Importantly, methenolone is already 5α-reduced, meaning it cannot be further converted by the 5α-reductase enzyme into a more potent androgen. This explains much of its mild androgenic character.
The anabolic-to-androgenic ratio of methenolone enanthate is typically cited as 88:44 to 88:57 when compared against testosterone as the 100:100 reference standard. In practical terms, this means the compound produces roughly 88% of testosterone's anabolic (muscle-building) activity while exhibiting only 44–57% of its androgenic (masculinizing) activity. It is worth noting that this ratio, while useful for comparing compounds, does not capture the full complexity of a steroid's behaviour in a living organism. Methenolone enanthate is not aromatizable-it does not convert to estrogen-which eliminates a whole category of estrogenic side effects.


Pharmacological Features and Advantages
The defining pharmacological feature of methenolone enanthate is its non-aromatizing nature. Because it cannot be converted to estradiol, users do not experience the water retention, gynecomastia risk, or blood-pressure elevation that accompany aromatizing compounds such as testosterone or Dianabol. The gains produced are therefore "dry"-that is, they consist primarily of contractile muscle tissue rather than subcutaneous fluid. This quality alone explains why methenolone became a staple of pre-contest preparation during bodybuilding's golden era and remains popular among physique athletes today.
A second feature is its low androgenic impact. While no anabolic steroid is entirely free of androgenic effects, methenolone's already-5α-reduced structure means it does not undergo further amplification in androgen-sensitive tissues. Acne, oily skin, and accelerated male-pattern hair loss are possible but generally dose-dependent and less pronounced than with more potent androgens. This makes methenolone enanthate a comparatively attractive option for women who wish to use anabolic compounds with a reduced risk of virilization, though caution remains essential.
Third, the enanthate ester provides a prolonged release profile. A single intramuscular injection maintains elevated blood levels for approximately two weeks, meaning injections need only be administered once or twice weekly. The 200 mg/ml concentration reduces the volume of oil that must be injected per dose, which is a practical consideration for users running higher weekly totals.
Finally, methenolone enanthate is not 17α-alkylated. Unlike oral methenolone acetate, which is modified to survive first-pass liver metabolism and therefore carries some hepatotoxic potential, the injectable enanthate bypasses the liver on its first pass and is considered essentially non-hepatotoxic at reasonable doses.
Bodybuilding Applications
Methenolone enanthate is most commonly employed during cutting or recomposition phases. Its combination of non-aromatization, mild androgenic activity, and appetite-stimulating effects makes it well-suited to diets that are calorically restricted. Users report that the compound helps preserve lean muscle mass during a deficit while contributing to a hard, dense appearance once body fat levels are already low. It is not a mass-building drug in the conventional sense; those seeking rapid size increases typically look to testosterone, nandrolone, or oxymetholone. Methenolone's contribution is one of quality rather than quantity.
Because it does not aromatize, methenolone enanthate is often stacked with a low dose of testosterone to maintain libido, mood, and overall hormonal balance. Running methenolone alone will suppress endogenous testosterone production, and since it provides no estrogenic support, users who suppress their natural testosterone without exogenous replacement may experience low-estrogen symptoms such as joint discomfort, lethargy, and diminished libido. The standard approach is therefore to include at least a replacement dose of testosterone in any methenolone-containing cycle.
Methenolone enanthate can also be used as a "bridge" compound between heavier cycles, though this practice is controversial. Its mild nature makes it less suppressive than many alternatives at low doses, but any exogenous androgen will exert some negative feedback on the hypothalamic-pituitary-gonadal axis.
Dosage Considerations
Dosage for methenolone enanthate is a subject of considerable debate. The compound is dose-sensitive: many users report that below a certain threshold, results are negligible. For men, commonly cited ranges begin at approximately 300–400 mg per week for beginners and extend to 600–800 mg per week for experienced users. Some sources suggest that 500–700 mg per week represents the "sweet spot" for most male bodybuilders. The 200 mg/ml concentration is convenient in this context: a 600 mg weekly dose requires only 3 ml of oil, which can be split into two injections of 1.5 ml each.
Women are advised to use substantially lower doses. Clinical and practical guidance suggests 50–100 mg per week, administered in a single injection or split into two smaller doses. Some clinical references recommend no more than 50 mg every two to three weeks for very lean women. Virilization risk, while reduced compared to more androgenic compounds, is not zero, and women should monitor for voice changes, clitoral enlargement, and unusual hair growth.
Injection frequency for the enanthate ester is typically once or twice weekly. Twice-weekly administration produces more stable blood levels, which may reduce fluctuations in mood and energy. Injection sites should be rotated to prevent scar tissue formation.
Cycle Design
A typical methenolone enanthate cycle for men lasts 10–16 weeks. Shorter cycles of 8–10 weeks are sometimes used, but because the enanthate ester takes several weeks to reach steady-state blood levels, shorter cycles may not allow the user to fully realize the compound's effects. A common framework is as follows: weeks 1–12 at 400–600 mg per week of methenolone enanthate, combined with a maintenance dose of testosterone (typically 150–200 mg per week) to preserve hormonal function. The cycle is followed by a waiting period to allow the ester to clear before initiating post-cycle therapy.
During the cycle, ancillary support is generally straightforward. Because methenolone does not aromatize, aromatase inhibitors are usually unnecessary. Lipid support-such as omega-3 fatty acids and citrus bergamot-is advisable, as anabolic steroids can adversely affect cholesterol profiles. Cardiovascular exercise and regular blood pressure monitoring are prudent practices for any cycle.
Half-Life and Pharmacokinetics
The elimination half-life of methenolone enanthate following intramuscular injection is approximately 10.5 days. This long half-life is a direct consequence of the enanthate ester, which slows the release of the active hormone from the injection depot. Peak plasma concentrations are typically reached several days after administration, followed by a gradual decline. The active life of a single injection is commonly cited as 10–14 days.
The long half-life has two practical implications. First, injections need only be administered once or twice weekly. Second, after the final injection, the compound remains in the system for a considerable period. This is why a waiting period of approximately 14–18 days is recommended before starting post-cycle therapy. Starting PCT too early, while methenolone is still suppressing the hypothalamic-pituitary-gonadal axis, would be counterproductive.
Methenolone is extensively metabolized in the liver, with the primary urinary metabolite being 3α-hydroxy-1-methylene-5α-androstan-17-one. Sulfated metabolites can be detected in urine for extended periods, with some markers remaining detectable for up to 17 days and others potentially longer.
Post-Cycle Therapy
Post-cycle therapy (PCT) is mandatory after any suppressive anabolic steroid cycle, and methenolone enanthate is no exception. Despite its reputation as a "mild" compound, it suppresses endogenous testosterone production, particularly at the doses used in bodybuilding contexts. PCT aims to restore the hypothalamic-pituitary-gonadal axis to normal function as quickly and safely as possible.
The standard PCT protocol following a methenolone enanthate cycle involves a selective estrogen receptor modulator (SERM). Nolvadex (tamoxifen citrate) is commonly used at 20 mg daily for four weeks, sometimes with a tapering scheme of 20/20/10/10 mg over four weeks. Clomid (clomiphene citrate) is another option, typically dosed at 50 mg daily for four weeks. Some practitioners prefer enclomiphene, a more targeted isomer of clomiphene, at 25 mg daily for two weeks followed by 12.5 mg daily for four weeks and then 12.5 mg every other day for one week.
The timing of PCT initiation is critical. Because methenolone enanthate has a half-life of approximately 10.5 days, it takes roughly five half-lives-about 50 days-for the compound to be almost completely cleared from the system. However, most practical protocols initiate PCT approximately 14–18 days after the last injection, when circulating levels have declined sufficiently to allow the SERM to stimulate gonadotropin release without being overwhelmed by ongoing androgen suppression.
During PCT, users should monitor for signs of low testosterone: fatigue, loss of libido, mood disturbances, and joint aches. Blood work-including total testosterone, luteinizing hormone, follicle-stimulating hormone, and estradiol-can provide objective confirmation of recovery. Full restoration may take several weeks to several months, depending on the individual and the duration of the preceding cycle.
Clinical Data
|
Brand |
STROMUSC |
|
Trade names |
Metenolone enanthate,Nibal Injection,Primobolan Depot Metenolone 17β-enanthate; NSC-64967; SH-601; SQ-16374; |
|
CAS |
303-42-4 |
|
Molar mass |
414.630 |
|
Formula |
C27H42O3 |
|
Purity |
Above 98% |
|
Capacity/Bottle |
200mg/ml |
Any needs, please contact us
Email: Jasonraws106@gmail.com
WhatsApp: +86-15572565525
Telegram: +86-15871669785


Conclusion
Methenolone enanthate 200 mg/ml is a compound that rewards patience and precision. It will not deliver the dramatic size gains of testosterone or nandrolone, but it offers something arguably more valuable to the physique-focused athlete: quality. The gains are lean, the side-effect profile is comparatively benign, and the non-aromatizing nature simplifies cycle management considerably. Its long half-life makes twice-weekly dosing practical, and its mild androgenic character makes it one of the few injectable anabolic steroids that can be considered for female use with appropriate caution. None of this means the compound is harmless. Suppression of natural testosterone production is real, cardiovascular and lipid effects require monitoring, and the compound remains a controlled substance in most jurisdictions. Used responsibly, however, methenolone enanthate remains a distinctive and enduring tool in the bodybuilder's pharmacological repertoire.
Hot Tags: premium brand stromusc primobolan(methenolone enanthate)200mg/ml for bodybuilding cas:303-42-4, China premium brand stromusc primobolan(methenolone enanthate)200mg/ml for bodybuilding cas:303-42-4 manufacturers, suppliers, factory

